Key Takeaways
- Agency selection should function as vendor risk assessment, not portfolio review, because HIPAA violations and FTC substantiation failures do not appear in polished case studies 5, 4.
- Score agencies against the four brand equity determinants that predict patient choice—perceived service quality, hospital image, patient satisfaction, and loyalty—so every criterion traces to admissions mechanics 3.
- Screen for regulatory fluency by requiring documented PHI workflows under HIPAA 5, FTC-grade substantiation files 4, SAMHSA-aligned incentive practices 7, and awareness of the Monument enforcement pattern 12.
- Map each claim category—outcomes statistics, alumni testimonials, clinician endorsements, and incentive messaging—to its specific evidentiary or consent artifact before creative work begins 4, 5, 7.
- Disqualify agencies that propose PHI-based audience building without authorization, offer outcomes statistics without substantiation, treat state statutes as edge cases, or dismiss the Monument settlement as isolated 5, 4, 1, 12.
- Use Texas HSC Chapter 164 as the drafting floor for multi-state work, since agencies that treat the strictest jurisdiction as an exception scope campaigns blind 1.
- Portfolio operators should require written state-statute inventories, portfolio-level PHI data-flow maps, and central endorsement registries rather than facility-by-facility documentation 1, 6, 4.
- Embed compliance obligations into contract terms and name kill criteria—unauthorized PHI disclosure, unsubstantiated claims, SAMHSA-inconsistent incentives, Monument-pattern data sharing—in the master agreement 6, 4, 7, 12.
Why Agency Selection Is a Due-Diligence Exercise, Not a Portfolio Review
Most agency shortlists get built the wrong way. A brand manager gathers case studies, admires the visual work, checks that the deck mentions HIPAA somewhere, and moves the strongest creative into finals. The problem is that healthcare branding sits on a legal and ethical surface that a portfolio cannot show. A campaign that looks polished on a website may have violated the HIPAA marketing definition the moment it repurposed a patient story without written authorization 5, or triggered FTC substantiation obligations by publishing an outcomes statistic without competent and reliable scientific evidence behind it 4. Neither failure appears in the case study.
Treatment center brand managers absorb that risk personally. When an agency proposes an alumni testimonial, an incentive-based message, or a clinician-fronted social campaign, the in-house team is the one signing off. That makes agency selection a vendor risk assessment, not a creative review. The disciplines are familiar to anyone who has scoped a clinical vendor: define the regulatory surface, require documented handling of protected health information, verify substantiation standards for every claim category, and confirm the agency recognizes state statutes that restrict addiction treatment advertising 1. Peer-reviewed work on healthcare promotion frames the baseline the same way—messaging is defensible only when it is truthful, non-discriminatory, and not misleading 2. The sections that follow translate that baseline into an evaluation framework built for compliance and admissions accountability.
Anchoring Evaluation Criteria to Brand Equity Drivers
The Four Determinants That Actually Move Admissions
The systematic review of hospital brand equity identifies four determinants that consistently predict how patients choose and re-choose a facility: perceived service quality, hospital image, patient satisfaction, and loyalty 3. Those four variables are the reason brand equity translates into census. When patients weigh a treatment center against alternatives, they are not comparing color palettes or tagline elegance; they are drawing on impressions of clinical competence, institutional character, prior experience, and the willingness to return or refer. The same review notes that strong brand equity strengthens patient trust and raises perceived prestige, which is the pathway from brand work to admissions volume 3.
For evaluation purposes, each determinant maps to a distinct agency capability. Perceived service quality requires messaging that reflects actual clinical protocols, staffing ratios, and modalities—content strategy work grounded in program specifics, not stock language about “personalized care.” Hospital image requires positioning and visual identity discipline that holds together across intake calls, alumni communications, and third-party review platforms. Patient satisfaction requires the agency to coordinate with clinical and operations leadership so that the brand promise does not outrun the lived experience. Loyalty requires post-discharge communication frameworks and alumni programs that respect HIPAA constraints on outreach 5.
Brand managers presenting an evaluation rubric to executives can trace every scoring criterion back to one of these four determinants. If a proposed criterion does not connect to service quality, image, satisfaction, or loyalty, it is likely measuring agency output rather than patient-choice mechanics.

Testing Whether an Agency Can Influence Those Drivers
A capable agency should be able to explain, in operational terms, how a proposed engagement moves at least one of the four determinants. Vague answers about “elevating the brand” or “telling your story” do not survive that test. Brand managers should ask the agency to walk through a prior engagement and identify which determinant the work targeted, what evidence was used to measure movement, and where the work fell short.
Perceived service quality is the easiest determinant to probe during a pitch. Ask the agency how it would substantiate a claim that a facility offers superior care. If the answer references outcomes statistics, the FTC standard of competent and reliable scientific evidence applies, and the agency should say so without prompting 4. Hospital image is harder to test but reveals itself in how the agency handles reputational risk—review response protocols, crisis messaging, and the boundary between promotional content and the truthful, non-misleading standard that peer-reviewed ethics work treats as the floor for medical promotion 2.
Patient satisfaction and loyalty require the agency to interact with data. Ask how it would segment alumni communications without triggering HIPAA’s marketing authorization requirement, which applies whenever protected health information is used to encourage recipients to purchase or use a service 5. An agency that cannot articulate that boundary is not equipped to build loyalty programs. The screening question is simple: can the agency name the determinant, the mechanism, and the evidentiary or consent burden without a lawyer in the room?
Regulatory Fluency: The Consolidated Compliance Screen
HIPAA Marketing Definition, Authorization, and PHI in Agency Workflows
HIPAA defines marketing as a communication about a product or service that encourages recipients to purchase or use it, and requires written authorization before protected health information is used or disclosed for that purpose, with limited exceptions 5. That definition is broader than most agency pitches assume. When a proposed campaign draws on admission records to segment past patients, when an alumni newsletter promotes a new IOP track, or when a retargeting audience is built from anyone whose data touched an intake form, PHI is in play and authorization becomes the operative question.
Brand managers should ask any agency to walk through, in writing, how PHI enters and exits its workflows. The answers should name specific systems: which CRM holds patient identifiers, who has access, how audiences are constructed for paid media, and where consent language for authorization lives in the intake flow. Agencies that describe segmentation using clinical data without addressing authorization are operating outside the rule.
The remuneration provision closes another gap. HIPAA treats a disclosure of PHI made in exchange for direct or indirect payment to another entity that will use it to encourage recipients to purchase a service as marketing with no exception—authorization is required in every case 6. That language matters when agencies propose data-sharing arrangements with lead aggregators, call centers, or third-party platforms. If the agency cannot describe the authorization mechanics for those flows, the arrangement is not defensible, regardless of the volume it promises to deliver.
FTC Substantiation, Endorsement Disclosures, and Implied Claims
The FTC’s Health Products Compliance Guidance sets two baseline requirements: advertising must be truthful and not misleading, and advertisers must hold competent and reliable scientific evidence for every objective product claim before dissemination 4. “Objective” is where agencies stumble. A claim that a program has a specific completion rate, that a therapy resolves a specific symptom, or that outcomes exceed a national average is an objective claim requiring substantiation. Aspirational language framed as fact carries the same burden.
Implied claims trigger the standard as well. A landing page that pairs a smiling alumni photo with the phrase “a new life” implies an outcome even if no percentage appears on screen. An agency should demonstrate that it screens copy for implied claims and maintains a substantiation file mapped to each claim in a live campaign. The absence of that file is the flag.
Endorsements and testimonials carry their own layer. The FTC requires clear and conspicuous disclosure of any material connection between an endorser and the advertiser, and advertisers are liable for misleading use of testimonials 4. Compensated alumni, staff members portrayed as third parties, and influencers with fee arrangements all fall inside that rule. Ask the agency to show its endorsement disclosure template, its process for verifying that a testimonial reflects a typical result, and its documentation of the endorser’s relationship. If those artifacts do not exist, endorsement work should be scoped out of the engagement.
SAMHSA, AMA, and Professional Ethics for Clinician-Fronted Campaigns
SAMHSA’s 2024 contingency management advisory draws a firm line: CM incentives must not be used to recruit patients into treatment or to advertise a practice 7. Agencies unfamiliar with behavioral health sometimes propose gift cards, milestone rewards, or referral bonuses as engagement mechanics. Applied to SUD populations, those tactics collide with the advisory’s coercion concerns and turn a clinical tool into a marketing liability.
The AMA’s advertising ethics opinion requires that physician communications be explicitly and implicitly truthful, and that a reasonable evidentiary basis exist for claims before they appear in advertising 8. That standard extends to any campaign that puts a clinician on camera, in a byline, or in a testimonial frame. The AMA’s direct-to-consumer opinion flags the risk of unrealistic expectations and compromised patient-physician relationships when persuasive messaging leads the creative 9, and its social media guidance directs clinicians to maintain patient-physician boundaries in online promotional contexts 10.
When agencies propose clinician-fronted content, brand managers should require full disclosure of financial arrangements and an evidence-based review of any product or program claim the clinician will make—the same standard the AMA has pressed for in resolutions on paid endorsements 11. Agencies that treat clinician talent as brand ambassadors without addressing disclosure and evidentiary basis are creating exposure the medical staff will inherit.
The Monument Case: What FTC Enforcement Actually Looks Like
In April 2024, the FTC settled a case against Monument, an alcohol addiction treatment firm, resulting in an order that bans the company from disclosing health information for advertising and requires affirmative consent before sharing health information with third parties for any other purpose 12. The order is the concrete answer to any executive who asks what regulatory risk actually looks like in this category.
The pattern that led to enforcement is familiar in agency pitches: pixels and tags on pages that capture health-related activity, audience objects synced to ad platforms, retargeting audiences assembled from users whose visits reveal sensitive conditions. Brand managers evaluating an agency should ask whether any prior client has removed a tracking pixel at counsel’s request, how the agency handles conversion tracking on pages that reveal diagnosis or treatment interest, and what its default position is when a platform’s targeting features require sharing health-adjacent data. An agency that treats the Monument outcome as a niche cautionary tale rather than a live operating constraint is not ready to run behavioral health accounts.
Mapping Claim Categories to Evidentiary and Consent Burdens
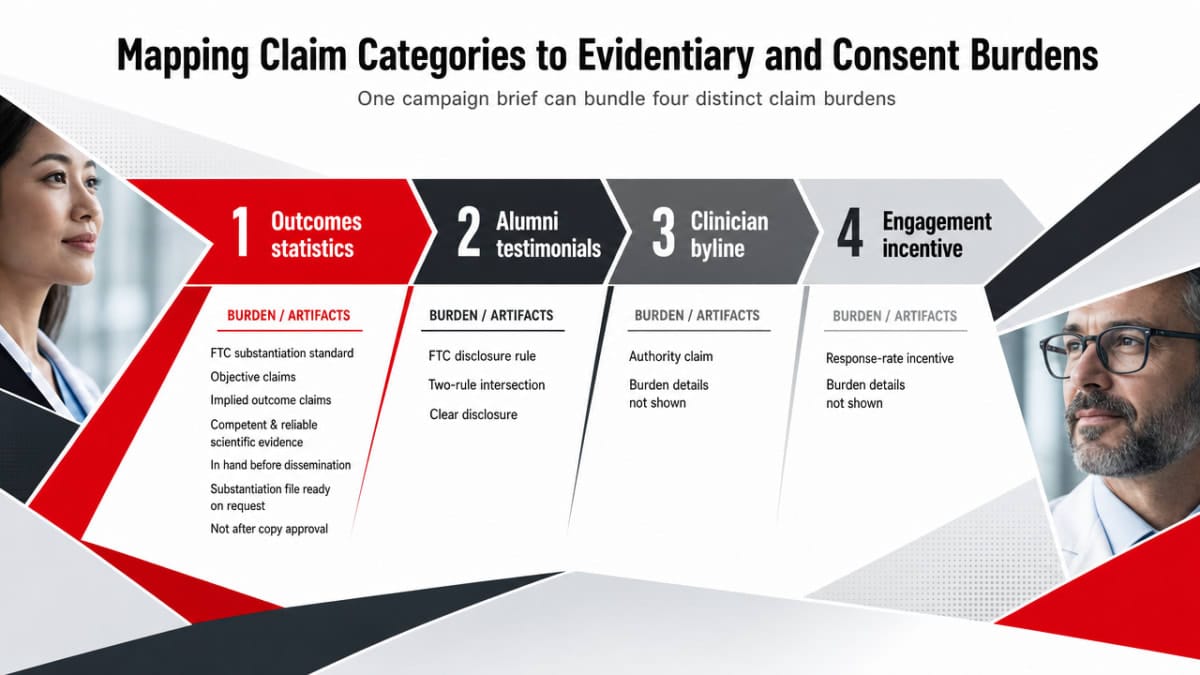
Agencies rarely propose one type of claim. A single campaign brief often bundles four: outcomes statistics on a landing page, alumni voices in video, a clinician byline for authority, and an engagement incentive to lift response rates. Each category triggers a different burden, and an agency that treats them as one problem will fail on at least three.
Outcomes statistics fall under the FTC’s substantiation standard. Any objective claim—completion rates, sobriety milestones, symptom reduction—requires competent and reliable scientific evidence in hand before dissemination, and implied outcome claims carry the same weight 4. The agency should be able to produce the substantiation file on request, not draft one after copy is approved.
Alumni testimonials sit at the intersection of two rules. The FTC requires clear disclosure of material connections and holds advertisers liable for misleading testimonials that do not reflect typical results 4. HIPAA then adds an authorization requirement whenever protected health information is used to encourage others to purchase or use a service, which is precisely what an alumni story does 5. Written authorization from the alumnus is not optional, and the authorization language must match the actual use.
Clinician endorsements bring professional ethics into the burden stack. AMA guidance requires clinicians on social platforms to preserve patient-physician boundaries and disclose compensation, and to avoid product claims that lack scientific validity 10. An agency proposing a physician-led series without a disclosure template and a claim-review process is proposing exposure the medical director will own.
Incentive-based messaging is the category most agencies underestimate. SAMHSA’s 2024 advisory is explicit that contingency management incentives cannot be used to recruit patients or advertise a practice 7. Referral bonuses, milestone gift cards presented as program features in ads, and “first-week-free” hooks in SUD contexts collide with that line.
A brand manager should hand the agency this four-category matrix during scoping and ask, for each row, which artifact—substantiation file, signed authorization, disclosure template, or advisory-compliant messaging guardrail—already exists in its workflow. Missing artifacts define what gets cut from the brief before the creative sprint begins.
Key Metrics to Assess in Healthcare Branding Agencies
Leverage data-driven branding strategies tailored for treatment centers to ensure measurable trust, compliance, and admissions growth.
Evaluate Your BrandDisqualifying Answers in the First Meeting
Some agency responses should end the conversation before a second meeting is scheduled. Brand managers running an evaluation benefit from naming these in advance so the pitch team hears the questions the same way legal and compliance will.
The first disqualifier is any proposal to use patient records for audience building without addressing authorization. When an agency describes uploading intake data to an ad platform, syncing a CRM containing PHI to a lookalike model, or building a retargeting audience from users who reached a diagnosis-specific page, the HIPAA marketing definition is triggered and written authorization is required with limited exceptions 5. An agency that describes this workflow without naming authorization is not describing a compliant workflow.
The second is a proposed outcomes statistic offered without a substantiation source. If an agency arrives with a suggested completion rate, recovery percentage, or comparative benchmark and cannot immediately name the study, dataset, or internal audit behind it, the FTC standard of competent and reliable scientific evidence is not being met 4. The same disqualifier applies to implied outcome claims that pair aspirational imagery with unverified language.
The third is treating state statutes as edge cases. Texas Health and Safety Code Chapter 164 restricts specific marketing and admissions practices at mental health and chemical dependency facilities, and other states carry parallel or stricter rules 1. An agency that describes multi-state work without a state-statute inventory is scoping blind.
The fourth is any framing of the 2024 Monument settlement as an isolated incident rather than a baseline expectation for consent-based data handling in this category 12.
State Statutes and the Portfolio-Operator View
Texas HSC Chapter 164 as a Benchmark for State Exposure
Texas Health and Safety Code Chapter 164 is worth reading not because every operator has a Texas facility, but because it shows how a state legislature translates general concerns about misleading treatment marketing into specific statutory prohibitions. The chapter’s stated purpose is to safeguard the public against fraud, deceit, and misleading marketing practices by prohibiting or restricting practices that have injured the public in connection with the marketing of mental health services and the admission of patients 1. Its definition of advertising is deliberately broad, reaching internet solicitations and media placements that agencies often treat as generic performance channels.
If You Manage Multiple Licensed Facilities Across States
This subsection shifts the reader from single-facility brand management to portfolio operators—health systems, multi-facility treatment groups, and behavioral health platforms running licensed facilities across several states. The evaluation framework does not change in principle, but three variables scale nonlinearly and should appear on the scorecard.
The first is state-statute exposure count. Each licensed jurisdiction adds a statutory surface the agency must map. A brand manager overseeing five states should require a written inventory identifying each state’s marketing statute, its definition of advertising, and its restrictions on referral, admission, and testimonial practices, using Chapter 164 as the reference format 1. Agencies unwilling to produce that inventory during scoping will not produce it under deadline pressure.
The second is PHI-handling surface area. Every additional facility multiplies the number of intake systems, CRMs, and consent flows the agency touches. HIPAA’s authorization requirement applies at each entry point, and the remuneration provision has no exceptions when PHI moves to a third party for marketing purposes 6. A portfolio-level data-flow map, not a facility-by-facility patchwork, should be a deliverable.
The third is endorsement inventory. Alumni testimonials, clinician bylines, and influencer relationships accumulate across a portfolio, and each carries its own disclosure and substantiation obligations under FTC guidance 4. A central registry, not distributed marketing files, is the operating standard.
Structuring the RFP: Scorecard, Contract Terms, and Kill Criteria
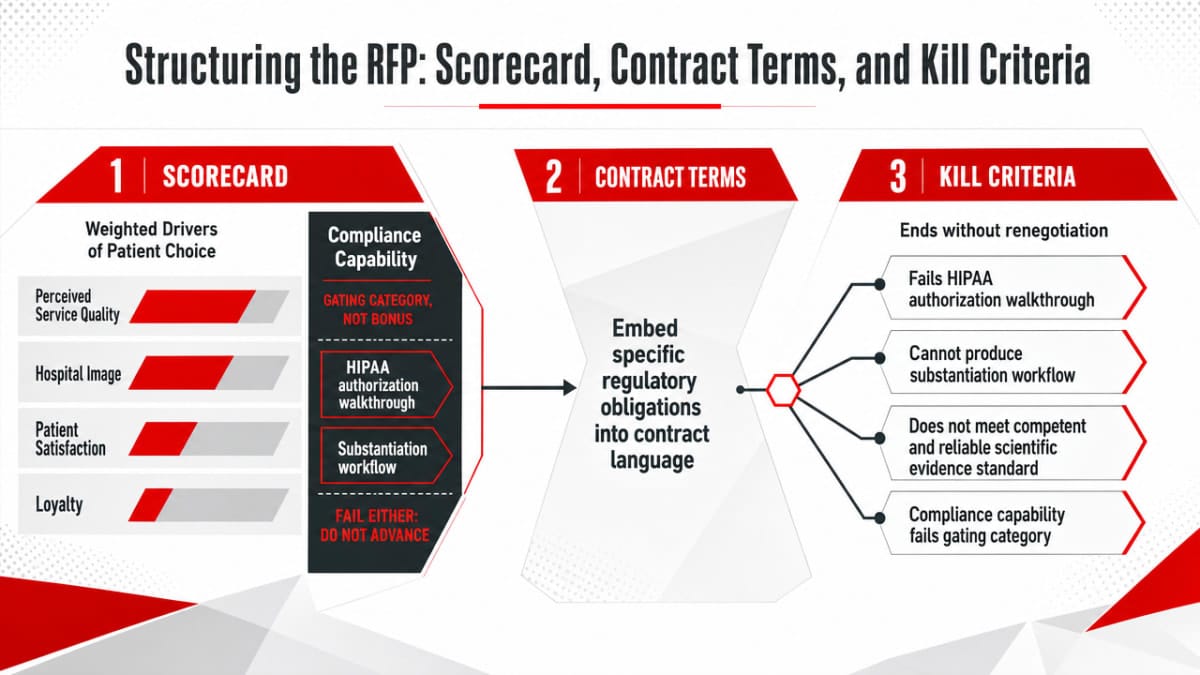
A defensible RFP does three things the standard template does not. It scores agencies against brand equity determinants rather than portfolio polish, it embeds specific regulatory obligations into contract language, and it names the conditions under which the engagement ends without renegotiation.
The scorecard should allocate weight to the four determinants that predict patient choice—perceived service quality, hospital image, patient satisfaction, and loyalty—so every criterion traces to a documented driver 3. Compliance capability sits alongside as a gating category, not a bonus: agencies that fail the HIPAA authorization walkthrough 5or cannot produce a substantiation workflow that meets the competent and reliable scientific evidence standard 4do not advance regardless of creative score.
Contract terms should codify what the pitch surfaced. Require a Business Associate Agreement covering every system that touches PHI, with the remuneration provision written in verbatim so downstream data-sharing arrangements trigger authorization by contract, not interpretation 6. Require a substantiation file as a deliverable for every objective or implied outcomes claim, with the file predating publication. Require endorsement disclosure templates and signed alumni authorizations as attachments to any testimonial deliverable. For multi-state operators, require a state-statute inventory refreshed annually, with Chapter 164-level jurisdictions treated as the drafting floor 1.
Kill criteria belong in the master services agreement, not the addendum. Termination for cause should trigger on any unauthorized PHI disclosure, any published claim without a pre-existing substantiation file, any incentive-based recruitment message inconsistent with SAMHSA guidance 7, and any data-sharing arrangement that would replicate the pattern the FTC sanctioned in the 2024 Monument order 12. Naming these conditions in writing shifts the conversation from good-faith reassurance to enforceable standard, which is the posture a brand manager needs when the campaign calendar starts pressing against the compliance review.
Frequently Asked Questions
What credentials or experience should a healthcare branding agency demonstrate before we shortlist them?
Require documented behavioral health engagements, a HIPAA-compliant data-handling workflow, and a substantiation process that meets the FTC standard of competent and reliable scientific evidence for objective claims 4. Agencies should also demonstrate familiarity with state marketing statutes such as Texas HSC Chapter 164 1and produce prior work that reflects the truthful, non-misleading floor for medical promotion 2.
How do we verify an agency actually understands HIPAA marketing rules and 42 CFR Part 2?
Ask the agency to define marketing under HIPAA, which covers any communication encouraging recipients to purchase or use a service, and to describe when written authorization is required 5. Then require a walkthrough of how PHI enters ad platforms, CRMs, and lead-sharing arrangements, since the remuneration provision requires authorization with no exceptions when PHI moves to a third party for marketing 6.
What level of substantiation should an agency require before proposing outcomes claims or alumni testimonials?
Objective outcomes claims and implied outcome claims require competent and reliable scientific evidence in hand before dissemination, with a substantiation file mapped to each claim in a live campaign 4. Testimonials add two layers: clear disclosure of material connections and evidence the story reflects a typical result 4, plus signed HIPAA authorization from the alumnus whose protected health information is being used 5.
Should we work with a generalist branding agency or one that specializes in behavioral health?
Specialization matters less as a credential than as a screen for regulatory fluency. A generalist that can define HIPAA marketing 5, meet FTC substantiation 4, and recognize SAMHSA guidance that CM incentives cannot be used to recruit patients or advertise a practice 7can execute the work. Agencies without that fluency inherit a learning curve the brand manager will pay for.
How should evaluation criteria change if we operate multiple licensed facilities across different states?
Three variables scale with the portfolio. State-statute exposure grows with each licensed jurisdiction, requiring a written inventory using Chapter 164 as the reference format 1. PHI-handling surface area expands with each intake system, and the remuneration provision applies at every entry point 6. Endorsement inventory across facilities requires a central registry with disclosure and substantiation documentation under FTC guidance 4.
What contract terms and kill criteria should we require in the agency agreement?
Require a Business Associate Agreement covering every system touching PHI, substantiation files predating publication of objective claims 4, and signed alumni authorizations attached to testimonial deliverables 5. Kill criteria should trigger on unauthorized PHI disclosure, published claims without a substantiation file, incentive-based recruitment inconsistent with SAMHSA guidance 7, and data-sharing patterns resembling the 2024 Monument enforcement order 12.
References
- HEALTH AND SAFETY CODE CHAPTER 164. TREATMENT FACILITIES MARKETING AND ADMISSION PRACTICES. https://statutes.capitol.texas.gov/Docs/HS/htm/HS.164.htm
- Ethical issues in advertising and promotion of medical units. https://pmc.ncbi.nlm.nih.gov/articles/PMC5711284/
- Consumer or Patient Determinants of Hospital Brand Equity: A Systematic Review. https://pmc.ncbi.nlm.nih.gov/articles/PMC9331757/
- Health Products Compliance Guidance. https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance
- Marketing (HIPAA Privacy Rule Guidance). https://www.hhs.gov/hipaa/for-professionals/privacy/guidance/marketing/index.html
- MARKETING [45 CFR 164.501, 164.508(a)(3)] Background (HIPAA). https://www.hhs.gov/sites/default/files/ocr/privacy/hipaa/understanding/coveredentities/marketing.pdf
- Advisory: Contingency Management for Substance Use Disorder Treatment. https://library.samhsa.gov/sites/default/files/contingency-management-advisory-pep24-06-001.pdf
- Advertising & Publicity | AMA Code of Medical Ethics. https://code-medical-ethics.ama-assn.org/ethics-opinions/advertising-publicity
- AMA Code of Medical Ethics Opinion 9.6.7: Direct-to-Consumer Advertisement of Prescription Drugs. https://policysearch.ama-assn.org/policyfinder/detail/direct%20to%20consumer?uri=/AMADoc/Ethics.xml-E-9.6.7.xml
- Physicians’ Use of Social Media for Product Promotion and Compensation. https://code-medical-ethics.ama-assn.org/ethics-opinions/physicians-use-social-media-product-promotion-and-compensation
- Resolution 025 (A-22): Physicians’ Online Product Promotion and Patient Information. https://www.ama-assn.org/system/files/a22-025.pdf
- Alcohol Addiction Treatment Firm Will Be Banned from Disclosing Health Data for Advertising to Settle FTC Case. https://www.ftc.gov/news-events/news/press-releases/2024/04/alcohol-addiction-treatment-firm-will-be-banned-disclosing-health-data-advertising-settle-ftc